
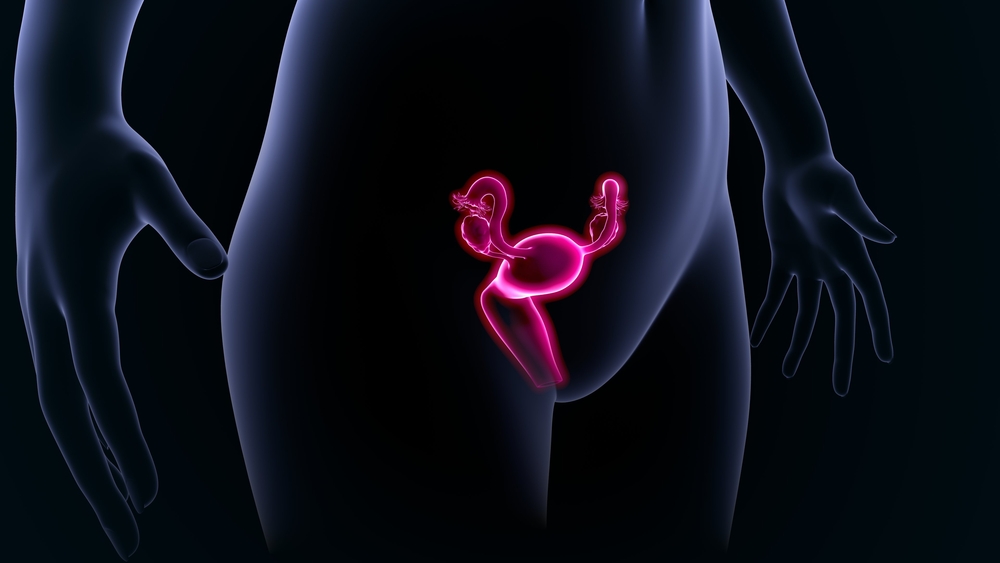
 Most gynaecological cancers are curable if caught early. Sadly, in some cases, the diagnosis is delayed. Sometimes this is due to patients not wanting to trouble their doctor with symptoms that they think are unimportant, or that they might be embarrassed about. Going for cervical smears regularly, watching your weight and telling your doctor about certain symptoms are the best ways of avoiding a delayed diagnosis.
Cervical cancer
The best way to avoid cervical cancer is to go for your cervical smears whenever asked to do so. Women aged between 24 and 50 years are invited for smears every three years, and those aged 50-64 years are invited every five years. Even if you go for smears regularly, it’s important not to ignore symptoms. Abnormal bleeding (i.e. bleeding between periods, after sex, or after the menopause), or an abnormal discharge are usually due to benign and easily-treatable causes, such as infections. Occasionally, they may be due to cervical cancer. The first step in checking for the cause of your symptoms is a vaginal speculum examination of the type used when a smear is taken. Remember that even if you are young enough to have received the ‘HPV’ vaccine at school, this does not prevent all cervical cancers, or other types of infection, so you should not ignore symptoms.
Who’s at risk?
Risk factors for cervical cancer include:
- Not having regular smears
- Smoking
- A poor immune system (e.g. someone with HIV or someone taking certain strong drugs used to suppress the immune system to treat a medical problem; never stop these drugs without discussing first with your doctor)
- Pelvic/lower tummy pain
- Tummy swelling/bloating
- Feeling full quickly after eating/nausea
- More rarely, ovarian cancer symptoms can include change in bowel and bladder habit (e.g. how often you need to go to the toilet, or a change in your bowel motions) and lower back pain
- Postmenopausal women (women who no longer get periods as a result of natural ageing)
- Women with a family history of ovarian/breast cancer especially at young ages (<50 yrs). This family history suggests they may have an inherited mutation in the BRCA1 or BRCA2 genes, which cause some breast and ovarian cancers. If you have a family history of these cancers (on your mother’s or father’s side), ask your GP whether you need to be referred to a Clinical Geneticist
- Women with Ashkenazi (Eastern European) Jewish heritage (up to 1 in 40 such women may carry inherited BRCA1 and BRCA2 gene mutations)[1]
- ‘Polycystic ovary syndrome’ (PCOS)
- Obesity
- Taking tamoxifen for treatment or prevention of breast cancer
- Taking certain types of hormone replacement therapy (HRT)
- Family history of bowel (especially if aged <50yrs), ovarian and womb-lining cancer. This suggests possible Lynch Syndrome; your GP should check how extensive your family history is and consider referring you to a Clinical Geneticist. Lynch Syndrome is under-recognised. It has been estimated that up to 1 in 500 of the population carry a mutation in one of the Lynch Syndrome genes[2]
- Previous precancerous changes on the vulva, cervix, vagina, or anus
- Smoking
- A poor immune system (e.g. someone with HIV or someone taking certain strong drugs used to suppress the immune system to treat a medical problem; never stop these drugs without discussing first with your doctor)
- Certain ‘auto-immune’ conditions, especially those affecting the skin e.g. lichen sclerosus
This article is for information only and should not be used for the diagnosis or treatment of medical conditions. myHealthSpecialist makes no representations as to the accuracy or completeness of any of the information in this article, or found by following any link from this article. Please consult a doctor or other healthcare professional for medical advice.
 Mr Adam Rosenthal, Consultant Gynaecologist
Gynaecological cancer
- Bahar AY et al. The frequency of founder mutations in the BRCA1, BRCA2, and APC genes in Australian Ashkenazi Jews: implications for the generality of U.S. population data. Cancer 2001;92:440-5
- Vasen HFA et al. Recommendations to improve identification of hereditary and familial colorectal cancer in Europe. Familial Cancer 2010;9:109–115